

Medical condition
Polymyalgia Rheumatica
Polymyalgia rheumatica causes severe shoulder and hip girdle pain and stiffness in adults over 50, worst in the morning. It usually responds well to corticosteroid treatment. New headache, scalp tenderness or visual change alongside it needs same-day assessment. Stiffness lasting over an hour makes rising, dressing and lifting the arms difficult.
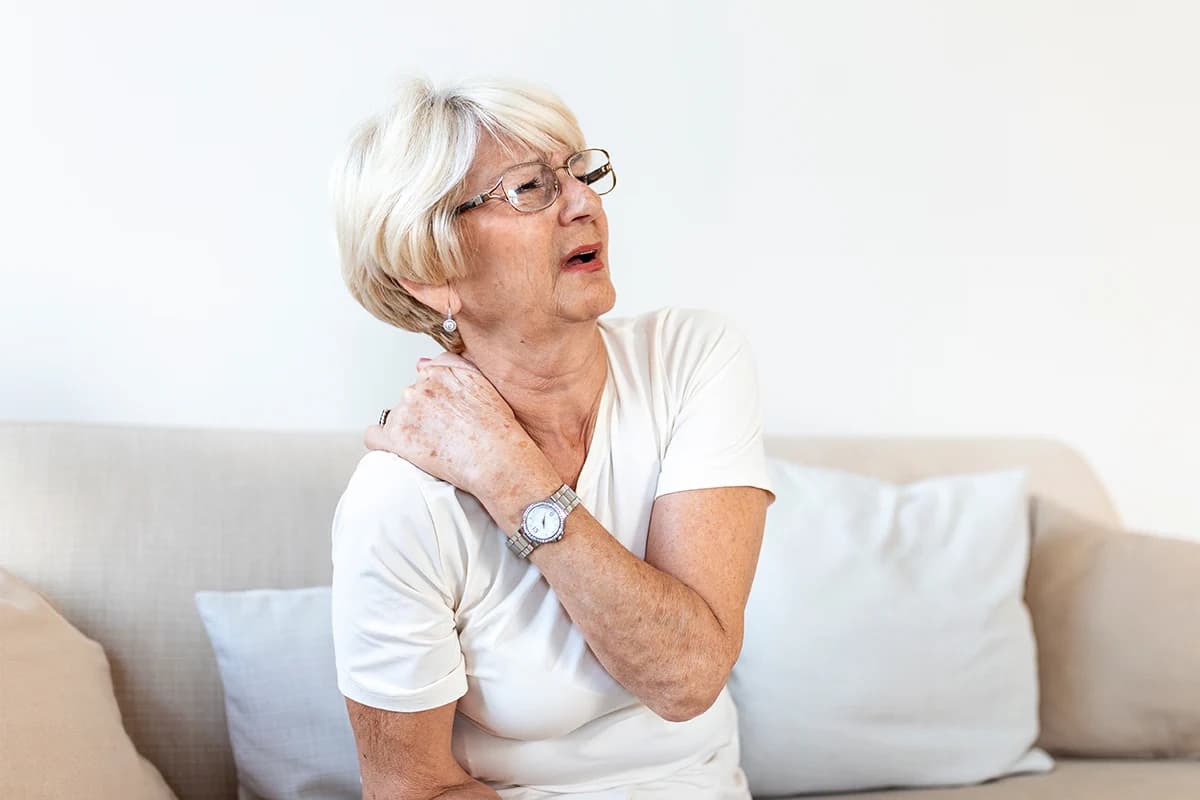
The pattern in an adult over 50
Pain and stiffness across both shoulders and often both hips, severe in the morning, making it hard to get out of bed, dress or raise the arms; the international classification criteria apply to people aged 50 or over and include morning stiffness lasting more than 45 minutes, and in the study behind them the median was two hours 2. Onset is often relatively sudden — people can date it to within a week or two.
It is accompanied by fatigue, sometimes low-grade fever and weight loss. Blood inflammatory markers are usually raised, which supports the diagnosis but does not make it alone.
The associated condition that is an emergency
Giant cell arteritis occurs in a proportion of patients with polymyalgia rheumatica. New headache, tenderness of the scalp or temples, jaw pain on chewing, or any visual disturbance require same-day assessment.
Untreated giant cell arteritis can cause sudden, irreversible loss of sight. This is the most important thing to know about polymyalgia rheumatica and it is why we lead with it.
Treatment and what rehabilitation adds
Most people improve markedly on corticosteroid treatment, but not all: in the study behind the international classification criteria, 71% had a complete response at four weeks, so the response alone does not confirm the diagnosis 2. Treatment is then tapered slowly over many months.
Rehabilitation works on maintaining range and strength during treatment, and on the muscle loss and bone loss that prolonged corticosteroid use causes. Resistance training and falls prevention matter here more than in most rheumatological conditions.
What to expect over time
Most people improve substantially and many can taper off steroids over one to two years 1. Relapse during tapering is common and is managed by adjusting the dose rather than by starting again.
Bone protection is considered from the start given the steroid course, and the risk of steroid-induced muscle weakness is one of the main reasons exercise is prescribed rather than suggested.
The complication that must not be missed
Giant cell arteritis occurs in a proportion of people with this condition and can cause permanent loss of sight, which is why European recommendations call for specialist assessment within 24 hours of suspicion, and for steroid treatment to start without waiting for test results when suspicion is strong 3.
New headache, scalp tenderness, jaw pain when chewing, or any visual change is an emergency requiring same-day treatment rather than an appointment. Every patient is told this explicitly.
How long does treatment last, and where does exercise fit?
Current European recommendations start treatment with 15 to 25 mg a day of prednisolone or an equivalent steroid 3. Guidance from Germany, Austria and Switzerland plans the reduction over 4 to 12 months, depending on whether a steroid-sparing drug is added 4. In practice, treatment often lasts longer than planned 5. For relapsing disease, or when the risk of steroid side effects is high, an interleukin-6 receptor blocker can be added, with methotrexate as an alternative 4.
Exercise does not treat the inflammation, but guidance recommends offering older and frail patients an individualised exercise programme 4. Its aim is to maintain muscle mass and function and to reduce the risk of falls during long-term steroid treatment 1.
Frequently asked questions
What are the warning signs of giant cell arteritis?
New headache, tenderness of the scalp, jaw pain on chewing, and any visual disturbance. These need same-day medical assessment because sight loss is irreversible.
How quickly does treatment work?
Most people improve markedly: in one international study, 71% had a complete response by four weeks 2. A poor response raises doubt about the diagnosis.
How long will I need steroids?
What does rehabilitation contribute?
Preserving strength and bone during prolonged steroid treatment, both of which steroids erode. This is where most of the long-term harm comes from.
Is it the same as fibromyalgia?
No. This is inflammatory, affects the shoulder and hip girdles in people over fifty, and responds rapidly to steroid.
Sources
- 2015 Recommendations for the management of polymyalgia rheumatica: a European League Against Rheumatism/American College of Rheumatology collaborative initiative — Annals of the Rheumatic Diseases (2015)
- Dasgupta B, Cimmino MA, Maradit-Kremers H, Schmidt WA, et al. 2012 provisional classification criteria for polymyalgia rheumatica: a European League Against Rheumatism/American College of Rheumatology collaborative initiative — Annals of the Rheumatic Diseases (2012)
- Mukhtyar CB, Nikiphorou E, Bartoletti A, Dey M, et al. 2025 EULAR recommendations for the management of polymyalgia rheumatica and primary large vessel vasculitis — Annals of the Rheumatic Diseases (2026)
- Buttgereit F, Boyadzhieva Z, Reisch M, Schneider M, et al. Recommendations of the German, Austrian and Swiss rheumatology and other medical societies for the management of polymyalgia rheumatica — Rheumatology (Oxford) (2026)
- Floris A, Piga M, Chessa E, Congia M, et al. Long-term glucocorticoid treatment and high relapse rate remain unresolved issues in the real-life management of polymyalgia rheumatica: a systematic literature review and meta-analysis — Clinical Rheumatology (2022)
Which therapies would I actually receive?
A therapy is a single method used inside a programme. It is measured in sessions and is not sold separately.
Technologies we use

Locations
Where you can receive this treatment






Related articles
Rheumatologic How long does polymyalgia rheumatica last?
Polymyalgia rheumatica usually responds quickly to steroid treatment, but the dose is reduced slowly and treatment often continues for a year or more. Relapses are common when the dose is lowered. Staying active and doing exercise that maintains muscle strength helps protect against the side effects of long-term steroids. Headache or vision changes need urgent attention.Read moreNeurological How long does it take to recover from a stroke?
Most recovery after a stroke happens in the early months, when the brain is most able to reorganise, and it continues more slowly for a longer period after that. How far someone gets depends mainly on how severe the stroke was, where it happened and how much active therapy follows.Read moreNeurological Can you walk again after a stroke?
Many people walk again after a stroke, including many who cannot stand at first. The chances are highest when some leg movement returns early and when walking practice starts as soon as it is safe. Walking often comes back before full arm recovery, sometimes with a stick, splint or other support.Read more



