

Medical condition
After Intensive Care
After a long intensive care stay, muscle loss, breathlessness, fatigue and impaired concentration occur together. Rehabilitation addresses all four at once over three to six weeks, starting at very low intensity and building. Swallowing is checked early, because it is often affected after prolonged intubation.

Surviving intensive care is not the end of it
People who leave intensive care frequently do so profoundly weakened. Muscle wasting starts early and fast: in one study of critically ill adults, a key thigh muscle lost 17.7% of its cross-sectional area within 10 days, and more in those with failure of several organs 2. Someone who spent two weeks ventilated may be unable to stand, swallow safely or manage stairs.
Alongside that there is often breathlessness, difficulty concentrating and memory problems, and significant anxiety. These are described together as post-intensive care syndrome, and they are common rather than exceptional.
Three problems that need treating together
Physical: profound weakness, loss of walking capacity, respiratory muscle weakness, joint stiffness, and frequently swallowing difficulty after prolonged intubation. Cognitive: reduced attention, slowed processing and memory difficulty. Psychological: anxiety, low mood and intrusive memories of the admission.
Treating only the physical side is the common failure. Someone who is walking again but cannot concentrate for long enough to work has not been rehabilitated.
How the programme is paced
Deconditioned patients fatigue quickly and recover slowly from overexertion, so intensity is built rather than assumed. Sessions start short and frequent, with careful monitoring, and lengthen as tolerance improves.
Respiratory muscle training, swallowing assessment where intubation was prolonged, progressive strength and endurance work, and graded return to daily activities. Where cognitive difficulty is present it is assessed rather than attributed to tiredness.
What to expect over time
Recovery from prolonged critical illness is measured in months, not weeks, and the trajectory is uneven. Families are often unprepared for this because discharge from intensive care is understood as the recovery, when it is the start of it.
We will give a realistic timeline at assessment and revise it against measured progress rather than leaving expectations unstated.
Three problems that arrive together
Physical weakness from critical illness myopathy, cognitive impairment and psychological effects including anxiety, depression and post-traumatic symptoms. The cognitive effects can be marked: in a large study, about a third of survivors still had cognitive scores typical of a moderate traumatic brain injury a year later 3.
They occur together and are frequently treated separately or not at all, because survivors are discharged from intensive care to a general ward and then home, with no one addressing the syndrome as a whole.
Does rehabilitation after intensive care make a difference?
Modestly, according to the randomised trials published so far. A 2024 meta-analysis of 14 randomised trials with 1,259 survivors found that exercise programmes started after hospital discharge produced small improvements in aerobic capacity and in the physical side of quality of life, and less depression, with no serious adverse events 5.
The psychological side has its own, smaller evidence base. In European studies, diaries kept during the intensive care stay were associated with fewer post-traumatic stress symptoms 4. Recovery is therefore planned across physical, cognitive and psychological needs, with the family included, rather than through exercise alone.
Frequently asked questions
Is fatigue after intensive care permanent?
Usually not, but it takes longer than people expect and it does not improve with rest alone. Pacing combined with graded activity is what changes it.
Why am I so weak after intensive care?
Muscle is lost rapidly during critical illness, and nerve and muscle damage from the illness itself compounds it. This is a recognised condition rather than deconditioning alone.
Will my thinking recover?
Often only partly. In a large study, about a third of survivors still had significant cognitive impairment a year after critical illness, and a longer period of delirium in hospital was linked to worse scores 3. It is worth assessing rather than waiting, so that difficulties with attention and memory are identified and planned for.
Are nightmares and flashbacks normal?
Common and treatable. About one in five survivors has clinically important post-traumatic stress symptoms a year after intensive care; earlier mental health problems, benzodiazepine sedation and frightening memories of the stay increase the risk 4.
How long does recovery take?
Months to over a year for many people. The trajectory is gradual and setbacks are part of it.
Does the family need support too?
Often. Relatives of intensive care survivors have high rates of anxiety and depression, and this is recognised as part of the syndrome.
Sources
- Rehabilitation after critical illness in adults (CG83) — National Institute for Health and Care Excellence (2009)
- Acute skeletal muscle wasting in critical illness — JAMA (Puthucheary ZA, Rawal J, McPhail M, et al.) (2013)
- Pandharipande PP, Girard TD, Jackson JC, Morandi A, et al. Long-term cognitive impairment after critical illness — New England Journal of Medicine (2013)
- Parker AM, Sricharoenchai T, Raparla S, Schneck KW, et al. Posttraumatic stress disorder in critical illness survivors: a metaanalysis — Critical Care Medicine (2015)
- Cazeta BBR, de Queiroz RS, Nacimento TS, Ferreira BR, et al. Effects of exercise interventions on functioning and health-related quality of life following hospital discharge for recovery from critical illness: a systematic review and meta-analysis of randomized trials — Clinical Rehabilitation (2024)
Which therapies would I actually receive?
A therapy is a single method used inside a programme. It is measured in sessions and is not sold separately.


Technologies we use
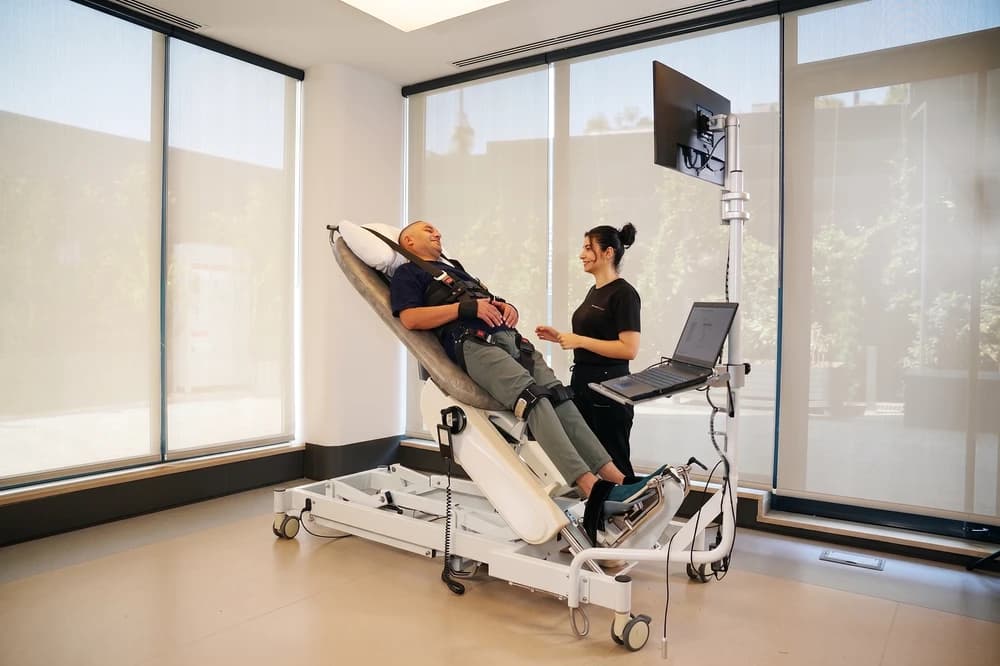


Locations
Where you can receive this treatment



Related articles
Geriatric Why do older people get weaker in hospital?
Older people often lose strength and independence during a hospital stay because of illness, bed rest and reduced movement. Even a short spell of bed rest can measurably reduce leg strength in healthy older adults. A substantial share of older patients leave hospital less independent than before. Moving during the stay helps prevent this.Read morePulmonary Why is recovery after intensive care so slow?
Critical illness and time in intensive care can cause lasting muscle weakness, fatigue, memory and concentration problems, anxiety, depression and post-traumatic stress, known as post-intensive care syndrome. In survivors of severe lung injury, physical function can remain below normal for years afterwards. Structured rehabilitation and follow-up support recovery.Read moreNeurological How long does it take to recover from a stroke?
Most recovery after a stroke happens in the early months, when the brain is most able to reorganise, and it continues more slowly for a longer period after that. How far someone gets depends mainly on how severe the stroke was, where it happened and how much active therapy follows.Read more



